

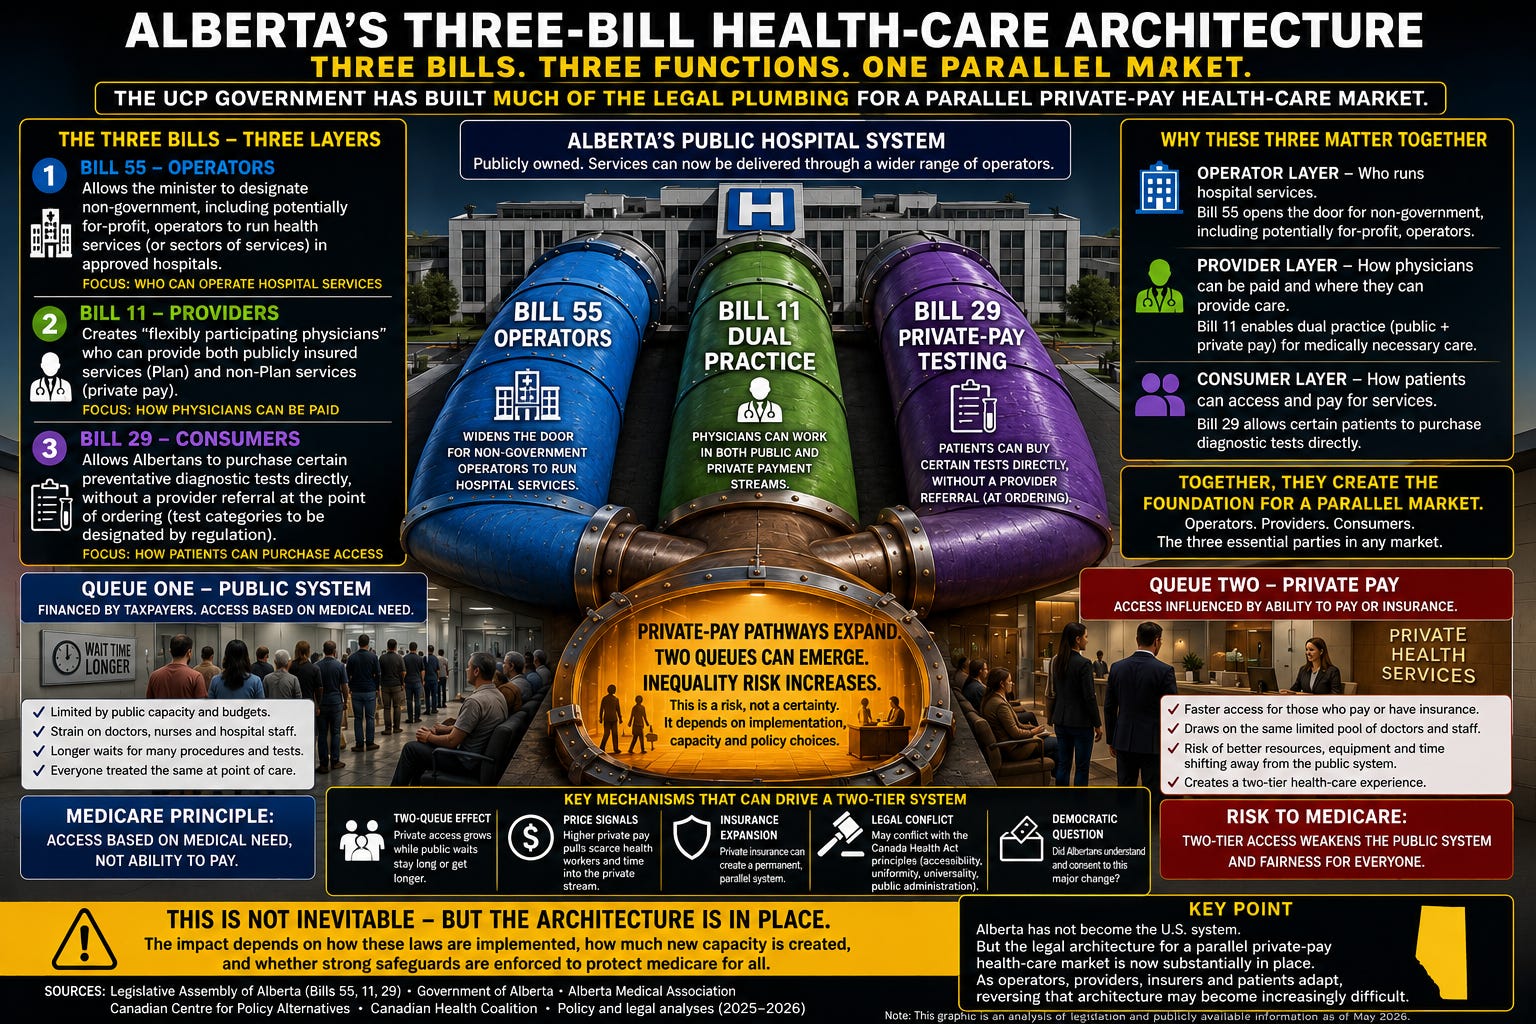
The graphic presents Alberta’s recent health legislation not as three isolated statutes, but as three interlocking parts of a possible parallel private-pay health-care market. Its central argument is that Bill 55 addresses who may operate hospital services, Bill 11 addresses how physicians may work across public and private payment streams, and Bill 29 addresses how patients may directly purchase certain diagnostic services. When these components are placed together, they form an operator, provider and consumer structure that resembles the essential institutional foundation of a market.
That interpretation does not mean Alberta has abolished public medicare, sold every hospital or converted its system into an American model. Publicly insured care remains the foundation of the provincial health system, and the legislation contains regulatory powers that could be used to limit private activity or protect public capacity. The graphic’s warning is subtler and more defensible: Alberta has established much of the legal machinery that could support a durable parallel market, and the eventual consequences will depend on regulations, contracts, workforce safeguards, enforcement and the extent to which private activity draws resources from the public system.
The graphic therefore contains two arguments at once. The first is descriptive, explaining what the legislation permits. The second is predictive, showing how the provisions could interact over time. The descriptive claims can be read directly from the statutes and government announcements. The predictive claims concern incentives, labour allocation, insurance development, unequal purchasing power and the long-term political resilience of medicare. Those outcomes are not automatic, but they are sufficiently plausible that they require serious public scrutiny.
The Public Hospital at the Centre of the Graphic
The hospital depicted behind the three pipes represents Alberta’s publicly owned and publicly funded health-care infrastructure. Its position is important because the graphic is not claiming that the public hospital has vanished. Instead, it shows new legal and commercial pathways being connected to an institution that remains public.
This distinction between public ownership, public financing and private operation is essential. A hospital building can remain publicly owned while particular services are delivered by a private company, charitable organization, professional corporation or contracted operator. Public money can finance a service performed in a privately operated facility. A privately financed service can also be provided by a physician who continues to work elsewhere in the publicly insured system. The labels “public” and “private” therefore describe several different dimensions rather than a single all-or-nothing choice.
Alberta’s restructuring has already separated major health responsibilities among specialized provincial organizations. Bill 55 was presented by the government as part of its broader effort to “refocus” and streamline the health system. The statute amended numerous laws and strengthened ministerial authority over the organization, designation and transfer of health functions. The government’s stated rationale was improved coordination, clearer responsibilities and better access for patients. Critics have focused on the accompanying power to designate operators outside the core provincial health agencies.
The public hospital in the graphic therefore represents the asset, workforce and clinical environment around which the new arrangements may operate. The pipes do not replace the hospital. They connect new operating, payment and purchasing possibilities to it.
Bill 55 and the Operator Layer
The blue pipe labelled “Bill 55 — Operators” represents the question of who may run hospital services. The relevant legislative language permits the oversight minister to designate a person other than a provincial health agency or provincial health corporation as an operator responsible for a health-services sector in an approved hospital. The minister must be satisfied that the operator is capable of delivering the applicable services, but the legislation leaves considerable room for ministerial decision-making and regulatory development.
The graphic accurately avoids saying that Bill 55 automatically transferred Alberta’s hospitals to corporations. Its wording is that the legislation “widens the door” for non-government operators, including potentially for-profit entities, to run hospital services. That is the more precise interpretation. The statute creates legal capacity rather than necessarily ordering an immediate system-wide transfer.
The importance of this distinction becomes clear when considering what “running hospital services” can mean. A designated operator might control staffing, scheduling, procurement, management systems, clinical workflow, equipment utilization or delivery standards for an assigned service sector. Even where the province retains ownership of the building and continues paying for insured patient care, operational authority can determine how resources are deployed and what organizational incentives shape daily decisions.
A non-profit operator may be driven by a public-interest or charitable mandate. A for-profit operator, by contrast, must ordinarily account for revenues, expenses, investor expectations or contractual returns. Profit does not automatically produce poor care, just as public operation does not automatically guarantee efficiency. The concern arises when financial incentives reward reduced staffing, increased throughput, selection of less complex cases or the separation of profitable services from costly ones.
The operator issue also concerns accountability. A provincial agency is subject to direct ministerial control, legislative scrutiny, public-sector reporting and access-to-information rules, although those mechanisms are not always complete. Contracted operators may introduce another institutional layer between elected government and service delivery. When failures occur, the government can blame the operator while the operator points to contract terms, funding constraints or government policy.
Bill 55 therefore alters more than the identity printed at the top of an organizational chart. It can alter the chain of accountability governing public hospital services. That is why the graphic identifies the legislation as the operator layer rather than merely an administrative reorganization.
Bill 11 and the Provider Layer
The green pipe labelled “Bill 11 — Dual Practice” represents physicians and the method by which they may be paid. Bill 11 introduced the statutory concept of a “flexibly participating physician,” establishing a framework under which eligible doctors may provide publicly insured services while also delivering designated services for private payment. The specific specialties, procedures, contractual conditions, geographic restrictions and public-service obligations depend on regulations and government policy.
The Alberta Medical Association describes dual practice as physicians working in both publicly funded and privately paid care. Alberta’s announced model initially focuses on elective surgery and requires participating physicians to maintain defined public-system commitments. The government has argued that this arrangement can attract physicians, use underutilized operating capacity, increase patient choice and allow those who pay privately to leave the public queue.
The graphic’s phrase “physicians can work in both public and private payment streams” captures the core structural change. Before this framework, Alberta physicians faced significant barriers when moving between participation in the provincial insurance plan and private billing for insured services. The new category is designed to permit simultaneous participation under controlled conditions.
This is arguably the most consequential of the three pipes because medical capacity ultimately depends on trained people. Hospital buildings, operating rooms, scanners and laboratories have limited value without physicians, nurses, technologists, anesthesiologists, pharmacists, cleaners and support staff. A private market does not automatically create an additional workforce; it creates another source of demand for the workforce already available.
The government’s strongest case is that dual practice may expand total supply. Higher earning opportunities could attract surgeons from other provinces or countries, encourage physicians to remain in Alberta, persuade semi-retired specialists to perform more procedures or support additional operating-room hours that would otherwise remain unused. Private spending could finance facilities and equipment without requiring the same level of immediate public capital.
The opposing case is that dual practice may redistribute scarce labour rather than create it. A surgeon who spends Friday in private practice may no longer be available for public surgery on Friday unless the private work is performed in genuinely additional time. Nurses and anesthesiologists recruited by private facilities may come from public hospitals. Diagnostic specialists may face increased private workloads while public vacancies remain unfilled.
The decisive measurement is therefore not the number of private procedures completed. It is the net change in total system capacity. A private clinic could perform 5,000 operations and still worsen public access if the staff required to perform those operations were drawn from public hospitals and the public system lost more capacity than it gained.
The Alberta Medical Association has approached the issue as one requiring extensive safeguards. Its task force developed approximately 70 proposed protections addressing equitable access, workforce sustainability, patient safety, accountability and the integrity of the public system. The existence of such a large safeguard package demonstrates that dual practice is not a minor billing adjustment. It is a significant change in the relationship between medical labour, public insurance and private purchasing.
Public-Service Requirements and Their Limitations
The government’s model does not offer participating physicians unrestricted freedom to abandon public practice. Regulations and contracts may require a minimum number of publicly funded procedures, establish limits on private volumes, exclude certain specialties or regions and restrict participation where public capacity is vulnerable. These powers are meaningful because they can determine whether private work becomes additional activity or merely replaces public work.
A minimum public-service requirement, however, does not by itself guarantee that public capacity will be protected. Suppose a surgeon currently performs 500 publicly funded operations each year and is later required to complete at least 350 before undertaking private work. The surgeon could comply with the requirement while public output falls by 150 cases. Conversely, a requirement that the physician maintain or increase their historical public volume before undertaking private procedures would offer stronger protection.
The choice of baseline is therefore crucial. Regulators must determine whether obligations are based on hours, procedures, historical production, regional needs, case complexity or combinations of those measures. Raw procedure counts can also mislead because ten uncomplicated operations do not necessarily consume the same resources as ten complex operations.
Monitoring must extend beyond physicians. A surgeon may maintain public volume while nurses, technicians or anesthesiologists reduce their public availability. The public-service obligation can appear successful when measured at the physician level even though the surrounding team has been weakened.
The graphic’s provider layer therefore includes more than doctor billing. It represents the allocation of the complete clinical workforce and the challenge of defining safeguards that operate across entire teams.
Bill 29 and the Consumer Layer
The purple pipe labelled “Bill 29 — Private-Pay Testing” represents patients as direct purchasers. Bill 29 amended Alberta legislation to create a framework for certain preventative health tests to be purchased privately without a provider referral. The government has stated that practitioner-recommended testing will remain publicly covered and prioritized and that regulations will define the eligible tests, conditions, reimbursement arrangements and operational requirements.
The graphic carefully says that patients may purchase “certain” tests and notes that categories will be designated by regulation. This qualification is essential because Bill 29 is enabling legislation. It lays the groundwork for a program rather than permanently specifying every test and every procedural detail in the statute.
The Alberta Medical Association identified MRI scans, CT scans and laboratory bloodwork as examples contemplated in the public discussion. Its concern is that direct access to testing does not necessarily produce better or faster care because diagnostic tests are parts of clinical pathways rather than self-contained consumer products.
A medically appropriate test begins with a clinical question. A physician or other qualified provider evaluates symptoms, risk factors, history and prior investigations before deciding which test is useful. The result must then be interpreted in context. A finding that appears alarming to a patient may be clinically insignificant, while a seemingly normal result may not rule out the condition under investigation.
Self-referral can therefore generate overtesting, incidental findings, false positives, false reassurance and duplicated investigations. These risks do not mean patients are incapable of making informed decisions. They mean diagnostic medicine is not equivalent to purchasing an ordinary retail service.
The graphic accurately says that the referral is removed “at the point of ordering,” rather than claiming that there is no medical oversight anywhere. A radiologist may still interpret an image, a laboratory professional may validate results, and a physician may become involved afterward. The concern is that the clinical assessment that traditionally precedes the test may be absent.
The Diagnostic Funnel and Downstream Public Costs
The private-pay testing pathway raises what may be called the diagnostic funnel problem. A patient pays privately for a scan or laboratory panel, but an abnormal, ambiguous or incidental result creates a series of downstream needs. These may include a family-physician appointment, repeat imaging, specialist consultation, biopsy, surgery, medication or long-term surveillance.
The initial transaction can be private while much of the resulting care is publicly funded. This does not necessarily make the initial test inappropriate, but it complicates the argument that private testing simply removes pressure from the public system. The private service may reduce one publicly funded test while increasing several publicly funded follow-up services.
For example, a whole-body scan may identify a small lesion that is statistically likely to be harmless. Because the possibility of serious disease cannot be dismissed, a physician orders another scan in six months, refers the patient to a specialist and discusses invasive testing. The patient has purchased earlier information, but the public system inherits the clinical obligation to resolve its meaning.
The opposite outcome is also possible. A privately obtained test may detect a serious disease early, permit less intensive treatment and reduce future public costs. The net effect depends on which tests are permitted, whether eligibility is risk-based, how patients are counselled and how results are integrated with primary care.
Bill 29’s impact therefore cannot be judged solely by counting privately purchased tests. Evaluation must measure diagnostic yield, false-positive rates, follow-up demand, duplication, patient outcomes and downstream public expenditures.
The Operator, Provider and Consumer Relationship
The upper-right portion of the graphic explains why the bills matter together. Bill 55 addresses the operator that organizes and delivers services. Bill 11 addresses the provider whose professional labour creates the clinical service. Bill 29 addresses the consumer who purchases access.
These are the three essential parties in a functioning market. An operator needs personnel and customers. Physicians require facilities, staff and a payment source. Patients require providers and places where services can be obtained. Each bill strengthens one side of this relationship.
Bill 55 alone could permit different operators without necessarily creating private patient payment. Bill 11 alone could permit physicians to receive private payment without creating widespread self-directed diagnostic purchasing. Bill 29 alone could allow privately purchased tests without changing hospital operation or surgical practice. Together, however, they create a more complete ecosystem in which private operators, dual-practice physicians and paying patients can interact.
This does not prove that every provision was enacted according to a single hidden privatization plan. Governments frequently pass interconnected legislation through separate statutes because different laws govern hospitals, professional payment and diagnostic services. Nevertheless, institutional effects do not depend on secret intent. The laws may form a coherent market architecture whether or not every detail originated from one master document.
The phrase “much of the legal plumbing” is therefore appropriate. Plumbing does not determine exactly what will flow through it, how much will flow or whether every valve will be opened. It creates pathways through which future policy can move.
Queue One and the Medicare Principle
The left side of the graphic depicts Queue One, the public system. It is financed mainly through taxation, and access is supposed to be based on medical need rather than the patient’s ability to pay. This is the moral and administrative foundation of Canadian medicare.
The Canada Health Act establishes federal criteria and conditions that provincial health-insurance systems must meet to receive their full federal health transfer. Its core principles include public administration, comprehensiveness, universality, portability and accessibility. The legislation also prohibits extra-billing and user charges for insured health services.
“Access based on medical need” does not mean every patient receives immediate treatment. Public systems ration scarce capacity through clinical priority, wait lists and budgetary decisions. A patient with an urgent condition should move ahead of someone whose condition can safely wait, regardless of income.
The graphic acknowledges the public system’s present limitations. Budgets constrain capacity. Workforce shortages restrict operating-room hours and diagnostic throughput. Many patients experience long waits. These are not imaginary problems invented to justify private reform. They are genuine failures that create public dissatisfaction and make private alternatives politically attractive.
The principle displayed at the bottom left is nevertheless decisive: people are treated under the same financial conditions at the point of insured care. A wealthy patient and a low-income patient enter the public queue according to clinical criteria rather than the size of their bank accounts.
Universality does not guarantee perfect equality. Rural patients may travel farther, well-connected people may navigate the system more effectively and educated patients may advocate more successfully. Public medicare’s promise is not that every social advantage disappears. Its promise is that the system does not officially sell priority for medically necessary insured care.
Queue Two and Ability to Pay
The right side depicts Queue Two, the private-pay pathway. Access is influenced by personal wealth or insurance coverage. The graphic does not say that every private service is medically necessary or that every private transaction violates federal law. It illustrates the broader equity difference between allocation according to need and allocation according to purchasing capacity.
A patient who can afford private testing or surgery may receive a service sooner. That patient benefits directly from reduced waiting and greater scheduling convenience. In some cases, the departure of paying patients from the public queue may shorten the queue for everyone else.
The problem arises when private access draws from the same restricted workforce and equipment pool. In that situation, Queue Two does not merely remove demand from Queue One. It also removes or competes for supply. Whether the public queue improves depends on which effect is larger.
A parallel market may also offer providers higher compensation, more predictable schedules, lighter emergency burdens and carefully selected patients. Private facilities can concentrate on elective, standardized procedures, while public hospitals retain trauma, complex illness, teaching obligations, intensive care and patients with multiple conditions. This creates a risk that profitable and predictable work migrates toward private settings while costly and difficult care remains public.
The resulting system could be financially asymmetrical. Private providers collect revenue from simpler cases, while taxpayers finance the infrastructure required for emergencies and complexity. This phenomenon is often described as cream-skimming, although the exact extent would depend on case-selection rules and contractual requirements.
The Two-Queue Effect
The central chamber states that private-pay pathways expand, two queues can emerge and inequality risk increases. The words “can” and “risk” are critical because the outcome is conditional rather than predetermined.
A two-queue system exists when patients seeking similar medically necessary services face different access pathways based partly on payment. One person waits in the publicly financed queue while another purchases earlier access from a physician or facility participating in the private stream.
The government’s case is that both queues can benefit if private activity expands total capacity. A private operation performed during an otherwise unused evening shift may add output without displacing a publicly funded case. A specialist attracted from another jurisdiction may divide time between public and private work while increasing the province’s total physician supply.
The critical case is that Queue Two will obtain its speed by taking time, staff or equipment from Queue One. The resulting private advantage would not come from newly created capacity but from preferential access to capacity that had previously served the public pool.
Evidence concerning parallel private systems is contested and depends heavily on institutional design. A recent CMAJ analysis argued that Canadian and international experience does not support the assumption that private-pay systems automatically reduce public waits. It emphasized that scarce professionals may move toward private work and that Alberta’s simultaneous public-private practice model goes further than systems where physicians must choose one sector.
The graphic properly treats the result as a danger requiring safeguards rather than a mathematical certainty. The policy test is whether Alberta can demonstrate measurable additional capacity while protecting or improving public performance.
Price Signals and Workforce Allocation
The dollar-sign mechanism in the graphic represents price signals. In economic terms, payment affects behaviour. Higher returns, better schedules and more attractive working conditions can draw workers and capital toward the private sector.
Physicians do not make decisions solely according to income. Professional ethics, commitment to public service, teaching interests, case complexity and workplace relationships all matter. Nevertheless, compensation and working conditions influence how medical labour is distributed, just as they influence every other labour market.
Suppose a public hospital offers a surgeon a demanding operating day involving emergencies, administrative duties and medically complex patients. A private facility offers scheduled elective cases, fewer disruptions and higher compensation. Even a physician strongly committed to public care may allocate some time to the private setting.
The effect extends through the team. Nurses may prefer regular daytime shifts. Anesthesiologists may choose predictable elective work. Technologists may leave understaffed hospitals for less stressful private facilities. The public institution can respond by increasing wages, improving schedules or purchasing services from the private provider, but each response carries fiscal consequences.
A private system can therefore raise the market price of scarce health labour. Higher compensation may improve recruitment, but it can also increase public costs merely to retain existing staff. Private investment is not costless to taxpayers when the public system must compete against it.
Insurance Expansion
The shield symbol in the graphic represents private insurance. Cash payment may initially limit private services to wealthy individuals, but insurance can broaden and normalize the market.
Once designated medically necessary services become legally available for private purchase, insurers may develop products covering those expenses. Employers may offer enhanced health-access benefits to executives or specialized employees. Unions may feel pressure to negotiate similar protection for their members. Families may purchase coverage out of fear that the public queue will not meet their future needs.
Insurance spreads the immediate cost of private care, but it also creates a permanent institutional constituency. Insurers, employers, clinics and covered patients acquire an economic interest in preserving and expanding the private system.
This can produce social segmentation. People with comprehensive employment benefits experience shorter waits and broader options. People employed precariously, living on disability benefits or unable to afford premiums remain dependent on public capacity.
Over time, private coverage may cease to feel optional. Families may conclude that responsible planning requires purchasing access insurance, much as they purchase dental or prescription coverage. A service once understood as a universal public entitlement becomes a benefit associated with employment or income.
The graphic therefore identifies insurance expansion as more than another method of payment. It can transform a limited cash market into a politically entrenched second system.
Legal Conflict and the Canada Health Act
The gavel symbol represents possible conflict with the Canada Health Act. The federal statute does not prohibit all private delivery or every private health service. Canada already has privately owned medical offices, pharmacies, diagnostic facilities and surgical centres that provide publicly funded care.
The central federal issue is patient charging for insured, medically necessary services. Extra-billing occurs when a physician or dentist charges an insured person more than the provincial plan pays for an insured service. User charges include other fees imposed as a condition of receiving insured care. Provinces allowing such charges may face mandatory dollar-for-dollar deductions from their Canada Health Transfer.
Federal enforcement has included deductions for private charges associated with medically necessary diagnostic imaging. In 2023, Health Canada announced more than $82 million in deductions, most of it connected to patient charges for diagnostic services.
The legal position of Alberta’s model will depend on how services are classified and structured. A privately purchased test that is not medically required, not insured under the provincial plan or undertaken as elective screening may be treated differently from a medically necessary diagnostic service. Similarly, private surgery outside the insured basket presents different questions from private payment for a service that remains provincially insured.
The federal government has recently clarified that charges for medically necessary services supplied by physicians or other professionals providing physician-equivalent services can trigger Canada Health Act consequences.
The graphic uses the word “may” because the existence of a conflict cannot be determined solely from the enabling statutes. It will depend on regulations, the designated services, actual billing practices and Health Canada’s enforcement position.
Public Ownership Does Not Resolve the Canada Health Act Question
A common misconception is that care remains compatible with medicare whenever it occurs inside a publicly owned hospital. Federal compliance is not determined only by who owns the building.
A patient charge for an insured service can raise Canada Health Act concerns even where the underlying facility is public. Conversely, a privately owned clinic may deliver a fully insured service without charging the patient and remain consistent with medicare requirements.
The significant variables are whether the service is insured, medically necessary, publicly covered and made available on uniform terms without extra patient charges. The graphic’s emphasis on operators, providers and consumers helps expose these separate dimensions.
The Democratic Question
The envelope and ballot symbol represent democratic consent. The issue is not whether Alberta’s elected government possesses legal authority to introduce health legislation. Provincial legislatures routinely restructure ministries, regulate physicians and amend insurance laws without holding referendums.
The democratic question is whether voters were clearly informed about the scale and direction of the changes. Did Albertans understand that government policy might permit simultaneous public and private physician practice? Did they understand that designated hospital-service sectors could be assigned to a broader range of operators? Did they understand that patients could purchase selected testing without referral?
Legislative debate provides formal democratic authorization, but formal legality does not settle the question of political mandate. A government may possess the votes required to enact a statute while still facing criticism that its election commitments did not adequately disclose the policy.
The complexity of omnibus health legislation compounds this problem. When a bill amends many statutes, the provision attracting the most attention may obscure other structural changes. Public consultation can be weakened when the government compresses debate, relies heavily on later regulations or presents each component as a narrow technical reform.
The graphic’s democratic concern therefore asks whether Albertans consented to the combined architecture rather than merely whether each bill passed through the Legislature.
The Risk to Medicare
The red panel states that two-tier access can weaken the public system and fairness for everyone. This warning concerns both material capacity and political solidarity.
The material risk is straightforward. If staff, operating time and diagnostic resources shift toward private-pay patients, public capacity may deteriorate. Wealthier patients escape the resulting delay, while those unable to pay remain exposed to it.
The political risk is longer-term. Universal programs remain strong partly because citizens across income levels depend on them. When affluent and influential people use the same schools, hospitals and public services as everyone else, they have a personal incentive to demand quality and adequate funding.
A parallel system can weaken that shared interest. People with private insurance or private access may become less concerned about public waiting times because they no longer experience them directly. Political pressure for public investment declines precisely among those with the greatest ability to influence policy.
The public system may remain formally universal while becoming a residual service for people who cannot purchase alternatives. This transformation need not occur through one dramatic legislative act. It can happen incrementally as private capacity expands and public expectations fall.
The graphic’s warning is therefore not that medicare will disappear immediately. It is that two-tier access can create a self-reinforcing cycle in which public deterioration generates demand for private escape, and private escape reduces pressure to repair the public system.
Wait Times and the Claim That Private Care Creates Relief
Long public waits are the strongest practical argument for reform. A patient living with pain does not experience the system as an abstract constitutional principle. The patient wants treatment.
Private-pay proponents argue that a patient who leaves the public queue frees a place for someone else. At the level of demand, this is correct. If all other conditions remain unchanged, removing one patient shortens the queue.
The problem is that all other conditions may not remain unchanged. If the physician, nurse and operating room also move partly into the private stream, the public queue may lose supply. The net effect depends on the balance between reduced demand and reduced capacity.
Consider a simplified example. One hundred patients are waiting, and the public system can treat ten each month. If twenty patients purchase private treatment using entirely separate staff and facilities, the remaining public queue falls to eighty and public access improves.
Now suppose those private services use personnel who previously provided two of the ten monthly public operations. Public capacity falls to eight. The public queue begins at eighty, but it is processed more slowly. The initial reduction may be offset over time by lost capacity.
The real analysis must therefore follow patients and resources simultaneously. Announcing that thousands of people were treated privately proves activity, but not necessarily public benefit.
The Possibility of Genuine Additional Capacity
A balanced analysis must recognize that private activity can be additive under carefully designed conditions. New facilities may extend operating hours. International recruitment may expand the workforce. Private capital may purchase equipment sooner than the public budget would. Contracts may require participating physicians to exceed their historical public output before accepting private cases.
The legislation’s consequences will therefore depend heavily on safeguards. Regulators could require proof that staff were newly recruited rather than taken from the public sector. They could establish public-volume floors, regional workforce protections, transparent wait-time reporting and restrictions on private recruitment from facilities experiencing shortages.
They could also require private operators to accept complex patients, contribute to training, maintain emergency arrangements and pay the full cost of complications or downstream care attributable to privately delivered procedures.
Without such rules, private operators may profit from narrow portions of the care pathway while relying on the public system for emergencies, complications, intensive care and follow-up. With strong rules, some private capacity could potentially supplement public service rather than hollow it out.
This is why the graphic concludes that the outcome is not inevitable. Architecture creates possibilities, but policy design determines how those possibilities operate.
Rural and Regional Consequences
Although rural Alberta is not depicted separately, it is contained within the graphic’s workforce and access concerns. Rural communities begin with thinner staffing margins, fewer specialists and longer travel distances. Losing even one physician, nurse or technologist can have a proportionally larger effect than a similar loss in Calgary or Edmonton.
Private-pay facilities are most likely to concentrate where there are enough customers, specialists and infrastructure to sustain them. That generally favours major urban centres. Rural patients with sufficient means may travel to purchase care, while those without transportation, time or money remain dependent on local public capacity.
If private opportunities draw professionals toward urban markets, regional inequality could worsen. Alternatively, the government could use participation rules, recruitment incentives or contractual obligations to direct additional service into underserved communities.
The geographic distribution of new capacity is therefore as important as the provincial total. Alberta could report an overall increase in procedures while some regions experience declining access.
Patient Safety, Continuity and Information Integration
The graphic’s three-pipe design also raises questions about continuity of care. A patient may receive a privately purchased test from one operator, interpretation from another physician and publicly funded follow-up from a third organization.
Health records must move accurately between these settings. Referring physicians must know what was ordered, why it was ordered and how the result should be interpreted. Private providers must have clear responsibility for urgent findings and must not simply direct every complication back to an already strained emergency department.
Continuity becomes particularly important when patients misunderstand the limits of screening. A negative test may create false reassurance, while an uncertain finding may produce anxiety. Proper consent requires an explanation of possible downstream consequences, including the fact that paying for a test does not necessarily guarantee immediate access to publicly funded follow-up treatment.
Quality standards must apply regardless of payment source. Private payment should not permit lower reporting standards, inadequate infection control, weaker credentialing or reduced disclosure of complications.
The AMA’s call for safeguards concerning patient safety, accountability, health information and workforce sustainability reflects these interconnected risks.
Financial Sustainability and Public Cost Shifting
The private-pay model is often presented as bringing new money into health care. That is true in the limited sense that households or insurers contribute funds that would otherwise not enter the system.
New money, however, is not the same as new resources. If private dollars purchase labour already financed, trained or supported by the public sector, the transaction may shift access without expanding supply.
Physicians are educated through heavily subsidized universities and obtain clinical training in public hospitals. Nurses, technologists and other professionals also receive publicly supported education. Private operators benefit from this publicly developed workforce.
Private facilities may additionally rely on public emergency departments, blood services, intensive-care units and tertiary hospitals when complications occur. Unless contracts assign those costs appropriately, the private operator retains revenue while taxpayers absorb part of the risk.
The province may also face higher labour costs as public employers compete with private compensation. What initially appears to reduce pressure on public budgets can produce new expenditures for retention, contracting and oversight.
The correct fiscal calculation must therefore include private spending, public savings, regulatory costs, workforce effects, complication costs and any increased public compensation required to maintain staffing.
The Difference Between Alberta’s Model and the United States
The graphic’s key point correctly states that Alberta has not become the United States. Alberta residents continue to receive broad coverage for insured physician and hospital services through the provincial system. Alberta does not presently rely on the American structure of employer-based primary insurance, extensive deductibles, multiple commercial payers and widespread medical debt.
The comparison with the United States is still relevant as a warning about market dynamics, but it must not be used as a literal description of Alberta’s current system. Alberta’s emerging model remains embedded inside Canadian constitutional, statutory and political institutions.
A more appropriate comparison is with other mixed systems that combine universal public insurance with regulated private alternatives. Those systems vary widely. Some maintain strong public access and tightly control private practice. Others experience substantial inequality, workforce diversion or dependence on supplemental insurance.
The outcome depends less on whether private activity exists than on its scale, regulation and relationship to public capacity.
The Meaning of “The Architecture Is in Place”
The lower banner states that the outcome is not inevitable but the architecture is in place. This is the graphic’s most important conclusion.
Architecture means the legal categories, operating permissions and payment relationships required for future expansion. Bill 55 provides an operator pathway. Bill 11 provides a dual-practice physician pathway. Bill 29 provides a direct patient-purchase pathway for designated testing.
Future governments can expand, narrow or repeal these pathways. Regulations may initially be cautious and later broadened. Services excluded today may be added tomorrow. Contracts may contain strong public protections or weak ones.
The legislation therefore matters even before the private market reaches large scale. Once clinics invest, physicians restructure their practices, insurers create products and patients rely on private options, reversal becomes harder. Businesses seek stability for their investments, professionals organize their careers around the new system, and insured patients resist losing access they have begun to use.
Legal architecture creates economic constituencies, and economic constituencies create political durability.
The Standard by Which the Policy Should Be Judged
The three-bill model should ultimately be judged through measurable outcomes rather than ideological labels. The central questions are whether public wait times improve, whether public procedure volumes are protected, whether the total workforce grows, whether rural access worsens, whether complications are shifted to taxpayers and whether low-income Albertans receive care under conditions equal to those available before the reforms.
Government should disclose the historical public volumes of participating physicians, changes in staffing at public facilities, recruitment sources for private operators, regional wait times, private prices, complication rates and downstream public costs.
The system should also be assessed for conflicts of interest. Physicians who can sell private services must not have incentives to lengthen public waits, steer patients toward affiliated facilities or recommend unnecessary testing. Waiting-list management should be independently audited, and patients should receive transparent information about both public and private options.
A credible program would include automatic suspension mechanisms when public access deteriorates. It would not merely promise safeguards; it would establish enforceable thresholds and publish the evidence required to determine whether those thresholds are being met.
Final Assessment
The graphic successfully captures a broad and complicated policy transformation in one coherent image. Its strongest insight is that Bill 55, Bill 11 and Bill 29 should be examined as interacting components rather than isolated reforms.
Bill 55 changes the range of possible hospital-service operators. Bill 11 changes the relationship between physicians and public or private payment. Bill 29 changes the capacity of patients to purchase designated testing directly. Together, these provisions establish much of the legal plumbing needed for a parallel private-pay market.
The case for the reforms is that private money, additional operators and flexible physician arrangements may increase capacity, attract professionals, provide choice and reduce public waiting lists.
The case against them is that the same changes may divert scarce workers, create two access queues, expand private insurance, shift complex costs back to taxpayers and weaken political commitment to universal public care.
Neither outcome should be declared inevitable in advance. The public consequences will be determined by implementation, workforce growth, regulatory strength, transparency and enforcement.
What cannot reasonably be denied is that Alberta has crossed an important structural threshold. The province is no longer debating private delivery only as a limited method of fulfilling publicly funded contracts. It is creating legal pathways through which operators may deliver services, physicians may work across payment streams and patients may purchase selected access.
The central issue is therefore not whether a private component exists somewhere in Alberta health care. Private delivery has existed for many years. The deeper question is whether private payment will remain a narrow supplement around the edges of medicare or develop into a parallel system that increasingly competes with it for workers, equipment, political attention and public confidence.
That question will define the meaning of these three bills long after their legislative titles have been forgotten.
Citationable Sources
Legislative Assembly of Alberta — Bill 55, Health Statutes Amendment Act, 2025. The enacted legislative framework addressing the restructuring of Alberta health organizations and the designation of operators for health-service sectors in approved hospitals.
Government of Alberta — Streamlining the Health Care System for Albertans. The government’s official description of Bill 55 and its role in Alberta’s health-system refocusing initiative.
Legislative Assembly of Alberta — Bill 11, Health Statutes Amendment Act, 2025 (No. 2). The primary legislative source establishing the framework for flexibly participating physicians and related regulatory powers.
Government of Alberta — Supporting a World-Class Health Care System. The province’s official explanation of Bill 11 and its intended modernization of physician-participation and health-system rules.
Alberta Medical Association — Dual Practice. The AMA’s description of Alberta’s public-private physician model, its implementation timetable and the meaning of dual practice.
Alberta Medical Association — Dual Practice Requires Strong Safeguards. The AMA’s discussion of its proposed safeguards concerning equity, workforce sustainability, safety, accountability and public-system integrity.
Alberta Medical Association — Dual Practice Models in Select Countries: Environmental Scan. A comparative assessment of international dual-practice systems, workforce implications, financial issues, patient safety and regulatory safeguards.
Alberta Doctors’ Digest — Possible Pros and Cons of Dual Practice. An explanation of Bill 11’s regulatory authorities, including specialty eligibility, contracts, volume requirements and geographic restrictions.
Legislative Assembly of Alberta — Bill 29, Health Statutes Amendment Act, 2026. The primary legislative source establishing the framework for designated preventative health-testing services.
Government of Alberta — Expanding Health Care Access for Albertans. The province’s official description of private preventative testing without referral and its Public Health Guarantee for practitioner-recommended testing.
Alberta Medical Association — Bill 29’s Proposal and Youth Proxy Access Update. The AMA’s analysis of direct patient purchase of MRI, CT and laboratory testing, including concerns about clinical interpretation and downstream system demand.
Canada Health Act. The federal framework establishing the conditions and criteria provincial insurance plans must satisfy to receive their full Canada Health Transfer.
Health Canada — Canada Health Act Annual Report 2024–2025. The federal explanation of extra-billing, user charges and the accessibility requirements applied to insured health services.
Health Canada — Statement from the Minister of Health on the Canada Health Act, January 2025. Federal clarification that patient charges for medically necessary physician and physician-equivalent services may be treated as extra-billing or user charges.
Health Canada — Letter to Provinces and Territories on the Importance of Upholding the Canada Health Act. Further federal clarification concerning charges for medically necessary services provided by physicians and other health professionals.
Health Canada — Reimbursement Policy for Provinces and Territories Subject to Canada Health Transfer Deductions. Explanation of mandatory dollar-for-dollar deductions where extra-billing and user charges are permitted.
Health Canada — Government Announces Deductions and Next Steps to Curb Private Health Care Paid Out of Pocket. Documentation of federal transfer deductions, including deductions connected to charges for medically necessary diagnostic imaging.
Canadian Medical Association Journal — A Parallel Private-Pay System Will Worsen Access to Publicly Funded Care. A 2026 examination of dual practice, health-workforce scarcity, public waiting times and evidence from Quebec and other jurisdictions.
Canadian Medical Association Journal — Restricting Private-Sector Practice Using Contracts. An analysis of contractual restrictions and the concern that dual practice may encourage providers to prioritize private patients and worsen public waits.
Canadian Medical Association Journal — Intervenors Decry Charter Challenge of Medicare. Discussion of the risk that private providers may select simpler and more profitable cases while complex patients and costs remain in the public system.
You have, once again, applied logic & fact to an emotional topic. Thanks.
I would like to add two points.
Costs. Requiring any activity to generate revenue will increase costs, all other aspects being equal. I have presented this simplified comparison many times & it still holds true.
Which costs more?
PROVIDE SERVICE = X$$$
OR
PROVIDE SERVICE + PROVIDE PROFIT = X$$$
Needs. The only reason there is a desire for private services is that the public service is not functioning as it should. Why would I pay for a hip replacement if I could get it done for free in the same time frame, with the same quality? We can resolve the debate by removing the need for private Healthcare. The Federal government could easily pay for the required system improvements.
What’s readily apparent is that if the ucp carry on the complexity, dare we say it red tape, is amplified exponentially all at the burden of the citizens.
Secondly by adding a for profit wing if you will you’ve now added two more bureaucratic layers, one on the government side for accountability, the second on the private side. Of course on top of this is the profit burden
Thirdly when you release control to private operators you’ve lost control of the process and the cost. There’s no comeback when the provider suddenly says I need/want 20% more and you’re in bed with them.
My solution is easier, cheaper, better.
I am very willing to pay for health care via my taxes. That way both I and all other Albertans can get the best and broadest of services
To that end we need INSTITUTIONAL professionals to game it out from policy to budget to implementation
Lastly every inept politician - that’s you ucp, who’s ever touched the health file needs to be fired.
This being at war with the public service, at war with Albertans and in service of friends/family and oligarchs has to end.
We have the resources, we have the people now we need the political will
Step away Danielle Smith, you couldn’t run a failed train car restaurant!